
"*" indicates required fields
Existing Patient Health History Form
Patient
Experience
Our Orthodontists Are Dedicated to
Providing the Best Patient Experience.
Our top priority is to provide you with the highest quality of orthodontic care in a warm and friendly environment.

#csorthodontics
Don't Wait

Actual Patient
Request a Complimentary Exam Today!
Our office provides high level orthodontic services by offering comprehensive solutions for all treatment types.
What our patients are

Best place ever! I never have pain in my mouth after every visit and my treatment is looking very good. Stuff in this clinic is absolutely incredible, everybody is very kind and great services!!

Andres A.
My son and I were at his location yesterday. Dr. Carroll and his entire staff are extremely professional. The service and care from beginning to the end of the appointment was very informative as to what treatment my son will need in the near future. We highly recommend Dr. Carroll.
JR B.
By far the best!! Dr. Carroll and his staff are amazing. They are friendly and kind. They take their time to make my son feel comfortable and explain everything I need to know. My son loves going here. Also, they are not out to do a bunch of stuff you don't need. I initially went here for a second opinion and I am so happy I did. It saved me a lot of money and was less traumatic for my son. I can't thank them enough!
Mike W.
By far the best!! Dr. Carroll and his staff are amazing. They are friendly and kind. They take their time to make my son feel comfortable and explain everything I need to know. My son loves going here. Also, they are not out to do a bunch of stuff you don't need. I initially went here for a second opinion and I am so happy I did. It saved me a lot of money and was less traumatic for my son. I can't thank them enough!
Lora A.
Dr. Aaron Carroll and his team are wonderful! 6 out of 5 stars if I could. He helped multiple members of our family and results were fantastic. Clean office and very professional care. Highly recommend!
Mina A.
I love this office soon much. JESS IS LITERALLY THE BEST. How often do people look forward to getting their braces tighten? Meee bc I love Dr Carroll and all of his people. I feel right at home with them!
Wara R.

Actual Patient
Follow Us
Instagram 





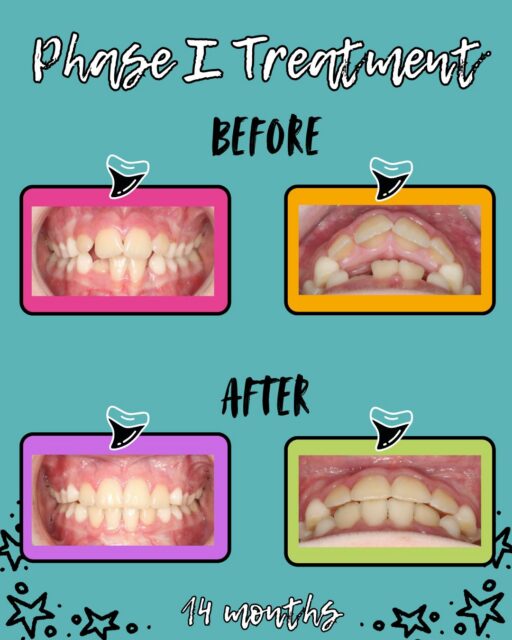


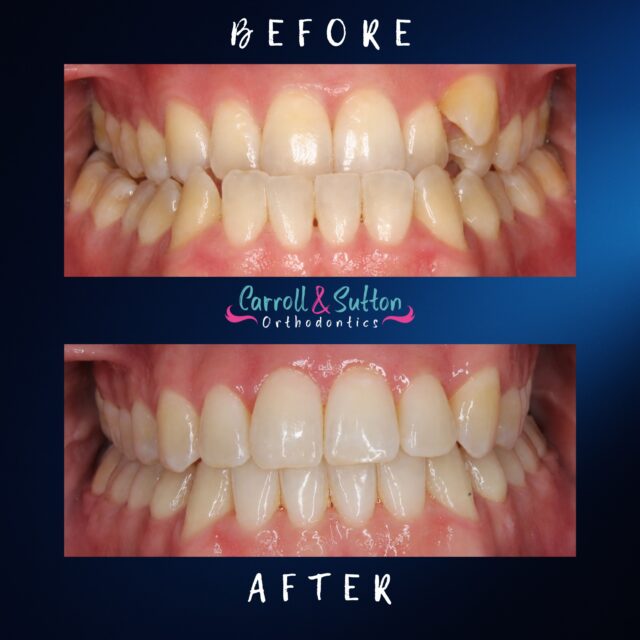


🎉💕 Happy 3-Year Work Anniversary, Francine! 💕
Three years of smiles, laughter, and being an amazing part of our CSO family! 🦷✨
We are so grateful for all your hard work, dedication, and the positivity you bring to our team every day.
Cheers to 3 wonderful years and many more to come! 🥳💗
Help us wish Francine a HAPPY WORK ANNIVERSARY! 🎉🎈
5 days ago


🏈 TOUCHDOWN! BRACES AND/OR ALIGNERS ARE OFF! 🏈
Every great smile is a team effort — and these patients showed up, stayed committed, and put in the work all season long! 💪😁
From the first appointment to the final check, we’ve been in this together. There were adjustments, challenges, and plenty of plays along the way, but our patients never gave up.
Today, we’re celebrating the big win: BRACES AND/OR ALIGNERS ARE OFF! 🏆✨
3 weeks ago

🎉 Congratulations to Our September Contest Winners! 🎉
Stay tuned for more fun contests and chances to win at Carroll & Sutton Orthodontics! 💙✨
3 weeks ago


Team Building + Coffee = The perfect combo!
Celebrating National Coffee Day with a little caffeine and a lot of laughs.☕🖤
4 weeks ago

🎉 Happy 9th Anniversary, Robyn! 🎉
Today we’re celebrating Robyn and 9 incredible years with our team! Thank you, Robyn, for your dedication, hard work, and all that you contribute each and every day.
We truly appreciate having you as part of the team and look forward to celebrating many more milestones with you. Congratulations on 9 years! 👏🎉
1 month ago
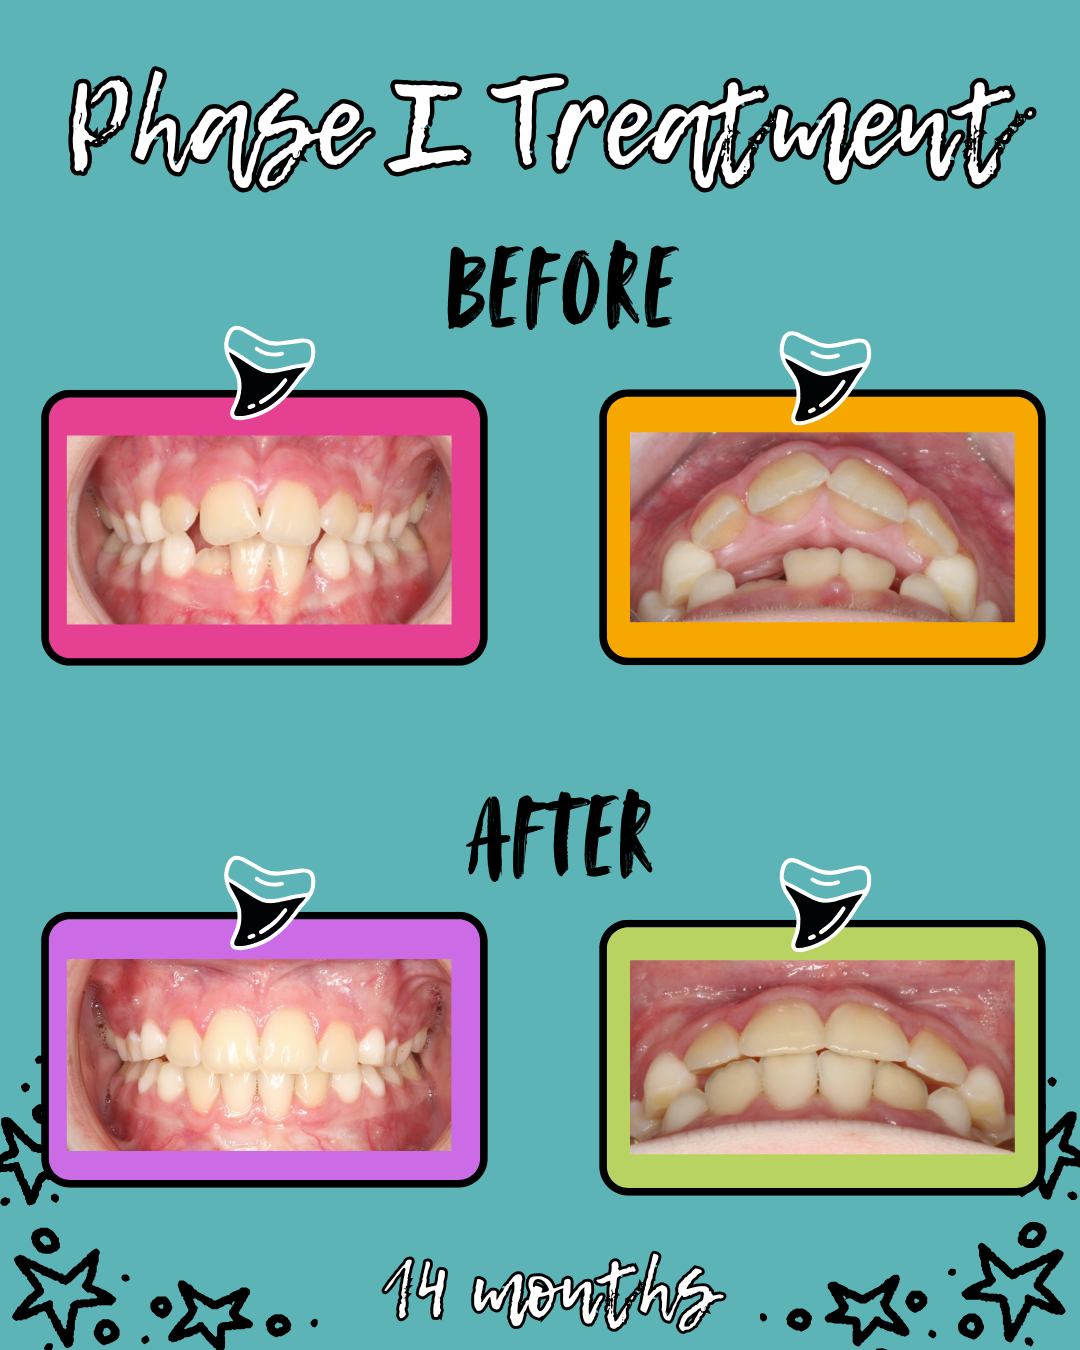
Happy birthday to our beloved Liss! 🥳
Wishing you the best birthday and amazing year ahead of you! We love you so much 💗
2 months ago
Smiles are definitely in season! 🍂
Celebrating some of our amazing patients who finished treatment and showing off their beautiful new smiles! 🤎
#FallSmiles #CarrollAndSuttonOrthodontics #Orthodontics #Ortho #fypシ❤️💞❤️
2 months ago


What a transformation! A beautiful before & after smile we’re so excited to celebrate! 😁🦷
#orthodontics #fypシ❤️💞❤️ #carrollandsutton #ortho #beforeandafter #transformation
2 months ago
facebook 
Tiktok 
Don't Wait
Request a Complimentary Exam Today!
Our office provides high level orthodontic services by offering comprehensive solutions for all treatment types.
What our patients are
Best place ever! I never have pain in my mouth after every visit and my treatment is looking very good. Stuff in this clinic is absolutely incredible, everybody is very kind and great services!!
Andres A.
My son and I were at his location yesterday. Dr. Carroll and his entire staff are extremely professional. The service and care from beginning to the end of the appointment was very informative as to what treatment my son will need in the near future. We highly recommend Dr. Carroll.
JR B.
By far the best!! Dr. Carroll and his staff are amazing. They are friendly and kind. They take their time to make my son feel comfortable and explain everything I need to know. My son loves going here. Also, they are not out to do a bunch of stuff you don't need. I initially went here for a second opinion and I am so happy I did. It saved me a lot of money and was less traumatic for my son. I can't thank them enough!
Mike W.
By far the best!! Dr. Carroll and his staff are amazing. They are friendly and kind. They take their time to make my son feel comfortable and explain everything I need to know. My son loves going here. Also, they are not out to do a bunch of stuff you don't need. I initially went here for a second opinion and I am so happy I did. It saved me a lot of money and was less traumatic for my son. I can't thank them enough!
Lora A.
Dr. Aaron Carroll and his team are wonderful! 6 out of 5 stars if I could. He helped multiple members of our family and results were fantastic. Clean office and very professional care. Highly recommend!
Mina A.
I love this office soon much. JESS IS LITERALLY THE BEST. How often do people look forward to getting their braces tighten? Meee bc I love Dr Carroll and all of his people. I feel right at home with them!
Wara R.
Actual Patient
Follow Us
Instagram
🎉💕 Happy 3-Year Work Anniversary, Francine! 💕
Three years of smiles, laughter, and being an amazing part of our CSO family! 🦷✨
We are so grateful for all your hard work, dedication, and the positivity you bring to our team every day.
Cheers to 3 wonderful years and many more to come! 🥳💗
Help us wish Francine a HAPPY WORK ANNIVERSARY! 🎉🎈
5 days ago
🏈 TOUCHDOWN! BRACES AND/OR ALIGNERS ARE OFF! 🏈
Every great smile is a team effort — and these patients showed up, stayed committed, and put in the work all season long! 💪😁
From the first appointment to the final check, we’ve been in this together. There were adjustments, challenges, and plenty of plays along the way, but our patients never gave up.
Today, we’re celebrating the big win: BRACES AND/OR ALIGNERS ARE OFF! 🏆✨
3 weeks ago
🎉 Congratulations to Our September Contest Winners! 🎉
Stay tuned for more fun contests and chances to win at Carroll & Sutton Orthodontics! 💙✨
3 weeks ago
Team Building + Coffee = The perfect combo!
Celebrating National Coffee Day with a little caffeine and a lot of laughs.☕🖤
4 weeks ago
🎉 Happy 9th Anniversary, Robyn! 🎉
Today we’re celebrating Robyn and 9 incredible years with our team! Thank you, Robyn, for your dedication, hard work, and all that you contribute each and every day.
We truly appreciate having you as part of the team and look forward to celebrating many more milestones with you. Congratulations on 9 years! 👏🎉
1 month ago
Happy birthday to our beloved Liss! 🥳
Wishing you the best birthday and amazing year ahead of you! We love you so much 💗
2 months ago
Smiles are definitely in season! 🍂
Celebrating some of our amazing patients who finished treatment and showing off their beautiful new smiles! 🤎
#FallSmiles #CarrollAndSuttonOrthodontics #Orthodontics #Ortho #fypシ❤️💞❤️
2 months ago
What a transformation! A beautiful before & after smile we’re so excited to celebrate! 😁🦷
#orthodontics #fypシ❤️💞❤️ #carrollandsutton #ortho #beforeandafter #transformation
2 months ago